
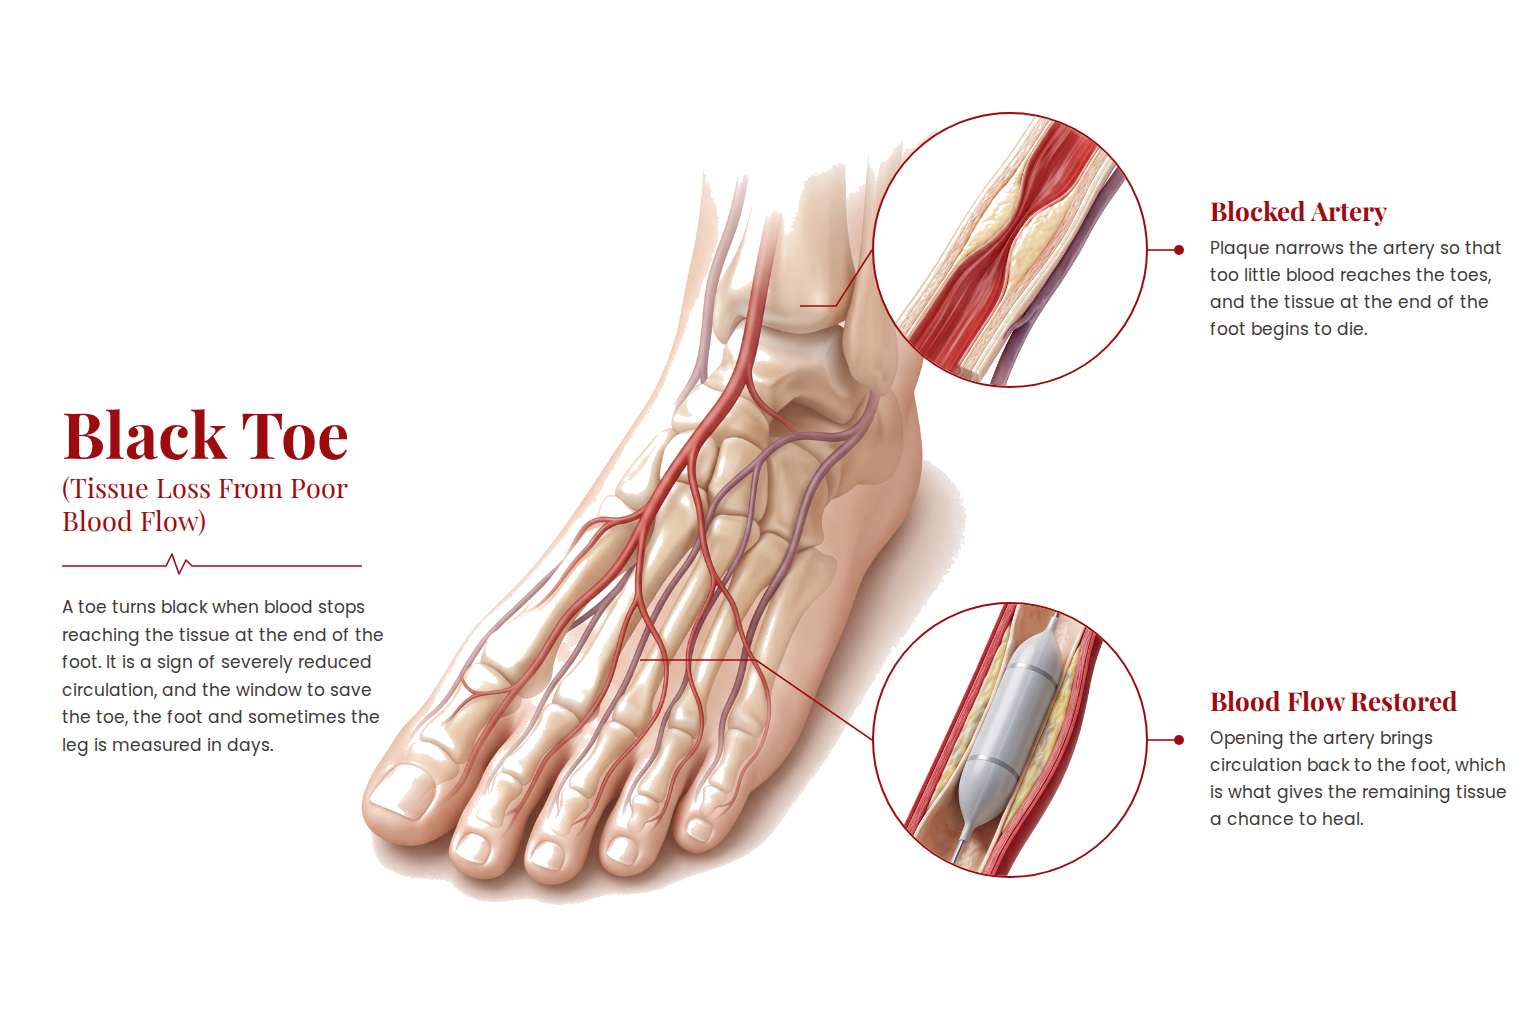
A toe that has turned black is one of the few things we ask patients to come in for the same week. It usually means tissue at the end of the foot has died because blood stopped reaching it, and the window to save the rest of the toe, the foot, and sometimes the leg is measured in days rather than months.
That is frightening, and we are not going to pretend otherwise. But a black toe is not the same thing as a lost leg. In most of the patients we see, the tissue around the dead area is still alive and can be saved, provided the circulation is restored quickly enough.
This article explains what a black toe means, which ones are emergencies and which are not, and what treatment involves. Then it walks through one of our own cases, step by step, with the imaging from the procedure.
If you are looking at a black toe right now, read the section on warning signs and then call us at 305-279-2621. The rest of this will still be here afterward.
Patient identifiers have been removed, and every case is different.
The main text is written for patients and families. A few sections end with a technical note for physicians. Skipping those costs you nothing.
A blocked artery in the groin, a puncture behind the knee, and blood back in the foot
The short version is that our team reopened an artery that could not be reached the usual way, and the foot got its blood supply back.
The main artery in this patient’s groin was completely blocked and could not be crossed from above, however it was approached. So we went in from behind the knee instead and worked back up the leg in the opposite direction, which is how the blockage was finally crossed. Once flow was restored at the top, we treated the diseased segment further down the thigh as well, so that the blood arriving had somewhere to go.
By the end, dye reached all the way into the foot where none had reached before. That does not guarantee a limb is saved, but it is the finding that makes healing possible at all.
What a black toe actually means
Living tissue needs a constant blood supply. When the arteries feeding the foot narrow or close, the tissue farthest from the heart starves first, and that means the toes. The color changes in stages, from pale to dusky to purple to black.
Black tissue is dead tissue. How deep that loss goes usually cannot be judged by looking at the surface, which is why surgeons wait until circulation has been restored and the border between dead and living tissue has declared itself before deciding what has to be removed.
There are two forms, and the difference between them matters a great deal.
Dry gangrene is dead tissue that stays dry, hard, and sharply bordered. It is serious and needs urgent attention, but it is not usually a same-day emergency.
Wet gangrene is dead tissue that has become swollen, wet, foul-smelling, or has started to drain. That means infection has taken hold, and it is a same-day emergency.
The underlying cause, in most cases, is peripheral artery disease, or PAD, which is plaque building up inside the arteries of the leg. In its most advanced form it is called chronic limb-threatening ischemia, or CLTI, and a black toe is one of the ways it announces itself.
CLTI means PAD confirmed on testing, plus at least one of three things: pain in the foot at rest that has been present for about two weeks, a wound on the foot or leg that has not healed in more than two weeks, or gangrene. The wound has to be caused by the poor circulation, because not every slow-healing foot wound is CLTI.
In earlier-stage PAD, blood flow is sufficient at rest and only falls short during walking, which produces cramping that eases when you stop. Many people with PAD have no leg symptoms at all, or have symptoms they put down to age or arthritis. That is a large part of why it often goes unrecognized until a wound appears.
Not every black toe is gangrene
Some causes are harmless, and it is worth knowing the difference.
A bruise under the nail. Doctors call this a subungual hematoma. It comes from stubbing the toe, dropping something on it, or repeated pressure from tight shoes while running or hiking. The black area sits under the nail, follows an injury you can usually remember, and grows out as the nail grows.
An ordinary bruise. Discoloration from a knock, which fades through the usual purple, green and yellow over a week or two.
Fungal nail disease. Chronic, slow to change, and painless.
One pattern deserves separate mention, because it fools people. In blue toe syndrome, a toe turns blue or black even though the pulses in the foot are still easy to feel. Small fragments of cholesterol debris have broken away from a plaque or an aneurysm higher up in the leg or abdomen and lodged in the tiny vessels of the toe. Normal pulses are not reassurance here, because the source further upstream still has to be found. This needs prompt vascular evaluation.
One more thing worth flagging. A dark streak or patch in the nail bed that is new, widening, or extends onto the skin at the base of the nail should be looked at by a dermatologist, because a melanoma of the nail bed can look exactly like a bruise that never grows out.
Warning signs and when to be seen
Go to the emergency department immediately, or call 911, if a foot suddenly becomes cold, numb, pale, or intensely painful. That pattern suggests acute limb ischemia, and it is measured in hours rather than days.
Go the same day for foul odor, drainage, spreading redness, or fever, which suggest infected gangrene or a spreading foot infection.
Call us promptly, within days rather than weeks, for a toe or part of the foot that has turned black, purple, or dusky without an obvious injury, for pain in the foot or toes at rest that is worse lying flat and eases when you hang the foot over the side of the bed, or for a foot wound that has not healed in two weeks.
Why diabetes changes the picture
Diabetes speeds up plaque build-up in the arteries below the knee that supply the foot, while usually sparing the arteries of the foot itself. That second part matters, because it is the reason catheter treatment and bypass surgery reaching all the way down to the foot remain possible. The older idea that diabetes closes off the tiny vessels of the foot beyond repair has been disproven, and it should never be the reason a limb is written off.
Diabetes also damages the nerves that would normally deliver a warning. Someone can develop a blister from a new shoe, never feel it, and come back weeks later with a deep infected wound and a blackening toe.
Daily foot inspection, including the soles and the spaces between the toes, using a mirror or asking a family member for help, is one of the most effective preventive steps available. It sits alongside glucose, blood pressure and cholesterol control, stopping smoking, properly fitted footwear, and regular professional foot checks.
How the circulation gets tested
The first tests are simple and involve no needles.
Ankle and toe pressures, called ABI and TBI, compare the blood pressure at the ankle and at the toe against the arm. Toe pressures matter especially in diabetes, because hardened arteries at the ankle can give a falsely reassuring reading.
Duplex ultrasound uses sound waves to find the blockages and grade how tight they are.
If treatment is being planned, a CT scan, an MRI scan, or a catheter angiogram maps the arteries in detail. An angiogram is an X-ray study taken while dye is injected into the arteries, so vessels that still carry blood show up as dark lines.
Specialists also stage the foot itself using a system called WIfI, which grades the wound, the degree of poor circulation, and any infection, and helps decide how urgently to act.
How we restored the blood flow, step by step
Step 1: an artery that could not be crossed from above

Figure 1. The groin artery could not be crossed from above.

Figure 2. Another angle. The artery was completely blocked.
The usual way to open a blocked leg artery is to work in the same direction blood normally flows, downward toward the foot. Doctors call that antegrade. When the blockage sits in the groin artery itself, that normally means going in through the opposite groin and crossing over the pelvis.
In this patient it did not work. The main artery in the groin, called the common femoral, was blocked along its whole length.
A blockage of long standing like this is called a chronic total occlusion. It is not a narrowing that a wire can be nudged through. It is a segment of artery sealed shut by hardened plaque and old clot, usually with a tough cap at the entrance. Coming at it from above means pushing a wire straight into that cap, and the cap tends to deflect the wire into the wall of the vessel rather than letting it through.
At that point there are three choices: send the patient for open bypass surgery, open the groin artery surgically, or find another way in.
| Clinical note. Chronic total occlusion of the common femoral artery is classic endarterectomy territory, and open CFA endarterectomy remains a durable, guideline-supported option. It is also a groin incision in a population that is frequently diabetic, obese, dialysis-dependent, or otherwise poorly suited to open wound healing. Antegrade failure here typically reflects a heavily calcified, eccentric proximal cap at the CFA origin just below the inguinal ligament, where wire escalation dissects into the subintimal space rather than finding the true lumen. Distally the bifurcation compounds the problem, since a subintimal wire preferentially tracks toward the profunda origin rather than re-entering the SFA. Repeated antegrade attempts raise the risk of dissection propagation and of losing the profunda, which is often the limb’s collateral lifeline. |
Step 2: going in from behind the knee instead

Figure 3. Access obtained to the popliteal artery, the artery behind the knee.
This is the point on which the case turns. Instead of approaching the blockage from above, we punctured an artery below the disease and worked backward, up the leg, toward it. That is called retrograde access.
Going in behind the knee carries meaningfully more risk than the standard groin puncture. The artery there sits in a tight space alongside a large vein and a major nerve, the patient usually has to lie face down, and bleeding in that space is harder to control by pressing on it than bleeding in the groin. The technique is not new, but it is one many practitioners avoid.
We offer it when the alternatives are open surgery or no treatment at all. Without restored circulation, a foot with dead tissue carries a high risk of amputation above the ankle.
| Clinical note. Retrograde popliteal access is performed under ultrasound guidance with the patient prone or in lateral decubitus, using micropuncture technique and a low-profile sheath. The relevant hazards are access-site specific: arteriovenous fistula given the immediately adjacent popliteal vein, pseudoaneurysm, tibial nerve injury (and common peroneal nerve injury with a more lateral approach), and the fact that a popliteal fossa hematoma occupies a confined compartment and is not reliably controlled by manual compression. Distal tibial or pedal access is an alternative retrograde entry point with a different risk profile, though it offers a smaller working channel. |
Step 3: crossing the blockage from the other direction

Figure 4. The blockage crossed from below.
The reason this works when the first attempt failed comes down to the shape of the blockage, which is not the same at both ends. The cap facing the oncoming blood flow from above tends to be dense, calcified and organized. The cap at the far end, approached from below, is usually softer and easier to penetrate.
Coming at the same blockage from the opposite direction turns a wire that kept sliding off into a wire that passes through. Nothing about the disease changed between the failed attempt and the successful one. Only the direction did.
| Clinical note. The asymmetry of cap morphology is the mechanistic basis for retrograde crossing. The proximal cap is remodeled under sustained antegrade pressure and tends to be fibrocalcific and convex; the distal cap is comparatively soft and more forgiving. Once traversed retrograde, the wire can be snared and externalized from the antegrade sheath, converting the case to a through-and-through system permitting stable device delivery from above. Where the retrograde wire tracks subintimally, controlled re-entry is required, and true-lumen position must be confirmed proximal to the lesion before balloon inflation. This family of techniques is described under the SAFARI and dual-access rubric. |
Step 4: flow restored at the top of the leg

Figure 5. Blood moving through the groin artery again.
For a patient with a black toe, this is the moment the outlook changes. Every decision that follows depends on blood arriving: whether a wound can close, whether removing a dead toe will heal rather than break down, whether antibiotics can even reach infected tissue.
Wound care alone does not heal a foot with no blood supply. Circulation comes first, and everything else follows from it.
Step 5: a setback, and why we are including it

Figure 6. The treated segment clotted off despite a good result.
The newly opened segment clotted shut.
We are including this deliberately. A case study that shows only the clean steps is advertising rather than education. This happens: a freshly treated artery has a raw inner surface, blood moving through a long reconstructed segment can be sluggish at first, and patients in this situation often have a tendency to clot, particularly with diabetes, kidney disease, or active inflammation.
What matters is that it is recognized and treatable when it is caught in the same sitting. It is one of the arguments for finishing the job with complete imaging rather than declaring success early and sending the patient home.
| Clinical note. Acute thrombotic closure after a technically successful intervention should prompt a search for a mechanical cause before it is attributed to hypercoagulability. The usual culprits are a flow-limiting dissection, elastic recoil in a heavily calcified segment, under-expansion, residual inflow disease, or inadequate outflow producing low shear. Management combines mechanical or aspiration thrombectomy, with or without catheter-directed lysis, plus correction of the underlying mechanical defect and attention to periprocedural anticoagulation and antiplatelet loading. |
Step 6: flow restored properly

Figure 7. Blood flow re-established after retreatment.
The goal is not a channel that looks acceptable on the table. It is a durable, brisk column of flow that will still be there when the patient walks into the follow-up appointment. Retreatment here means clearing the fresh clot and correcting whatever mechanical problem allowed it to form in the first place.
Step 7: treating the disease further down the leg

Figure 8. Severe disease lower down the thigh artery.

Figure 9. The same segment after treatment.
Patients in this situation rarely have one blockage. They usually have several at once, at different levels of the leg. Correcting the one at the top is reasonable and often necessary, and on its own it can relieve rest pain. But in a foot that has already lost tissue it is frequently not enough. If the vessels below stay blocked, the newly opened segment carries blood that has nowhere to go, and an artery with poor outflow is an artery with slow flow, which invites it to clot again.
Treating the inflow and the outflow in the same sitting is what produces a result that lasts. The full range of techniques we use is described on our chronic limb-threatening ischemia page, including balloon treatment, atherectomy, stents, pedal loop reconstruction, and, for selected patients with no remaining artery in the foot, deep venous arterialization.
| Clinical note. The Global Vascular Guidelines formalize this with the Global Limb Anatomic Staging System (GLASS), which grades femoropopliteal and infrapopliteal disease together to define a preferred target arterial path rather than a single culprit lesion. Inflow correction without outflow correction produces a hemodynamically disappointing result and a thrombogenic segment. Angiosome-directed revascularization remains debated; inline flow to the foot by any route is the more consistently supported objective. |
Step 8: blood reaching the foot

Figure 10. Blood flow reaching the foot, where none had reached before.
Final imaging showed dye reaching the foot where none had reached before. In limb salvage work, that finding is a positive predictor for preventing an amputation.
We word that carefully on purpose. Restored blood flow does not guarantee that the limb is saved. What it does is turn an outcome that was likely, meaning a major amputation, into one that is now possible, meaning a healed wound and a working foot. Healing still depends on wound care, infection control, taking pressure off the wound, blood sugar control, and overall health. None of those can succeed without the blood supply this case restored.
If part of a toe cannot be saved, removing only that portion after flow has been restored, so the site can actually heal, often preserves the foot and the ability to walk. Restoring circulation first is frequently what turns a below-knee amputation into a toe amputation.
| Clinical note. Post-revascularization the foot should be restaged. WIfI (Wound, Ischemia, and foot Infection) restaging after flow restoration, together with objective perfusion measures such as toe pressure or transcutaneous oxygen tension, guides both the timing and the level of any minor amputation. Wound healing timelines should be counted from the point of restored perfusion, not from initial presentation. |
What this case shows about saving a leg
Three things generalize beyond this patient.
A black toe is an endpoint, not an early warning. The disease that produces it develops silently over years, and the same process is frequently present in the arteries of the heart and brain. Anyone who presents this way needs their overall cardiovascular risk managed, not just a procedure on the leg.
Not being able to open an artery one way does not mean it cannot be opened. The first attempt in this case failed, and it is documented on imaging from two angles. A patient told at that point that nothing could be done would have faced an amputation. The artery was opened from the other direction.
Team-based care with a complete plan is the model that works. Current guidelines specifically recommend multispecialty care involving vascular specialists, podiatry, and wound care, and this model is associated with higher rates of limb salvage.
Black toe treatment in Miami: talk to a vascular specialist
At MVM Heart, Vein and Vascular Centers, our team pairs advanced diagnostics with compassionate, personalized care. We see patients at offices in Kendall (Miami) and Homestead, Florida, and serve Miami-Dade and the Florida Keys.
If you or someone you love has a blackening toe, a wound that will not heal, or foot pain at rest, please do not wait to see whether it settles on its own. If you have already been told that nothing can be done for the circulation in the leg, bring us the imaging before an amputation is scheduled.
Request a consultation or call 305-279-2621. We see patients at both our Kendall and Homestead offices. See our insurance information or download new patient forms before your visit.
Referring physicians: we accept urgent limb salvage referrals and will see wound and rest pain patients quickly. See information for referring physicians.
Frequently asked questions
Does a black toe always mean amputation?
No, it does not. When circulation can be restored in time, many limbs are saved. How likely that is depends on the pattern of the blockages, how much tissue has already been lost, whether infection is present, and overall health. Amputation is generally a last resort, used when blood flow cannot be restored or when severe infection threatens the patient’s life.
I was told my artery could not be opened. Is a second opinion reasonable?
Yes. As this case shows, a blockage that cannot be crossed from one direction can sometimes be crossed from another, and techniques such as retrograde access behind the knee or in the foot, pedal loop reconstruction, and deep venous arterialization have widened what is treatable. Whether any of them applies to you depends entirely on your own anatomy, and a review of your existing imaging can answer that.
How quickly do I need to be seen?
Within days rather than weeks. If the foot is also suddenly cold, numb, or severely painful, or if you have a fever and spreading redness, go to the emergency department now.
Can a black toe turn pink again?
Tissue that is truly black is dead and will not recover. How deep that loss goes usually cannot be judged from the surface, which is why surgeons wait for circulation to be restored and for the area to demarcate before deciding what has to be removed. The dusky, painful tissue around it very often does recover once blood flow returns.
Is this done under general anesthesia?
These procedures are usually performed with local anesthesia and sedation rather than general anesthesia, which is one reason they can be offered to patients considered too high-risk for major open surgery.
Can this be prevented?
Often, yes, by finding and treating peripheral artery disease before it reaches this stage. Controlling diabetes, blood pressure and cholesterol, stopping smoking, wearing properly fitted footwear, and checking the feet daily all substantially reduce the chance that PAD progresses to a limb-threatening stage.
Related reading
Peripheral Artery Disease · Critical Limb Ischemia · Vascular Ulcers · Carotid Artery Disease · Patient Education · Our Services
This article describes a de-identified case and is provided for general educational purposes. Individual anatomy, treatment options, and outcomes vary, and no specific result is implied or guaranteed. This is not a substitute for personalized medical advice. Always consult a qualified healthcare provider about your specific condition.
References
Gornik HL, et al. 2024 ACC/AHA/Multisociety Guideline for the Management of Lower Extremity Peripheral Artery Disease. *Circulation.* 2024;149(24):e1313-e1410. https://www.ahajournals.org/doi/10.1161/CIR.0000000000001251
Conte MS, et al. Global Vascular Guidelines on the Management of Chronic Limb-Threatening Ischemia (SVS/ESVS/WFVS). *J Vasc Surg.* 2019;69(6S):3S-125S. https://pubmed.ncbi.nlm.nih.gov/31159978/
Farber A, et al. Surgery or Endovascular Therapy for Chronic Limb-Threatening Ischemia (BEST-CLI). *N Engl J Med.* 2022;387(25):2305-2316. https://www.nejm.org/doi/full/10.1056/NEJMoa2207899
Fitridge R, et al. The intersocietal IWGDF, ESVS, SVS guidelines on peripheral artery disease in people with diabetes mellitus and a foot ulcer. 2023. https://iwgdfguidelines.org/wp-content/uploads/2023/07/IWGDF-2023-05-PAD-Guideline.pdf
Schaper NC, et al. Practical guidelines on the prevention and management of diabetes-related foot disease (IWGDF 2023 update). *Diabetes Metab Res Rev.* https://onlinelibrary.wiley.com/doi/full/10.1002/dmrr.3657
Society for Vascular Surgery. Chronic Limb-Threatening Ischemia (patient information). https://vascular.org/patients-and-referring-physicians/referring-physicians/who-refer/patients-chronic-limb-threatening
Disclaimer: This article is general educational information, not medical advice for any specific person. For personalized guidance, please schedule a consultation or talk to your physician.
Disclaimer: This article is general educational information, not medical advice for any specific person. For personalized guidance, please schedule a consultation or talk to your physician.