By the time patients reach us for this conversation, somebody has usually already said the word amputation. The angiogram comes over, which is the X-ray study that maps the arteries with dye, and the note says no distal target. The plan is a below-knee amputation, meaning taking the leg above the ankle.
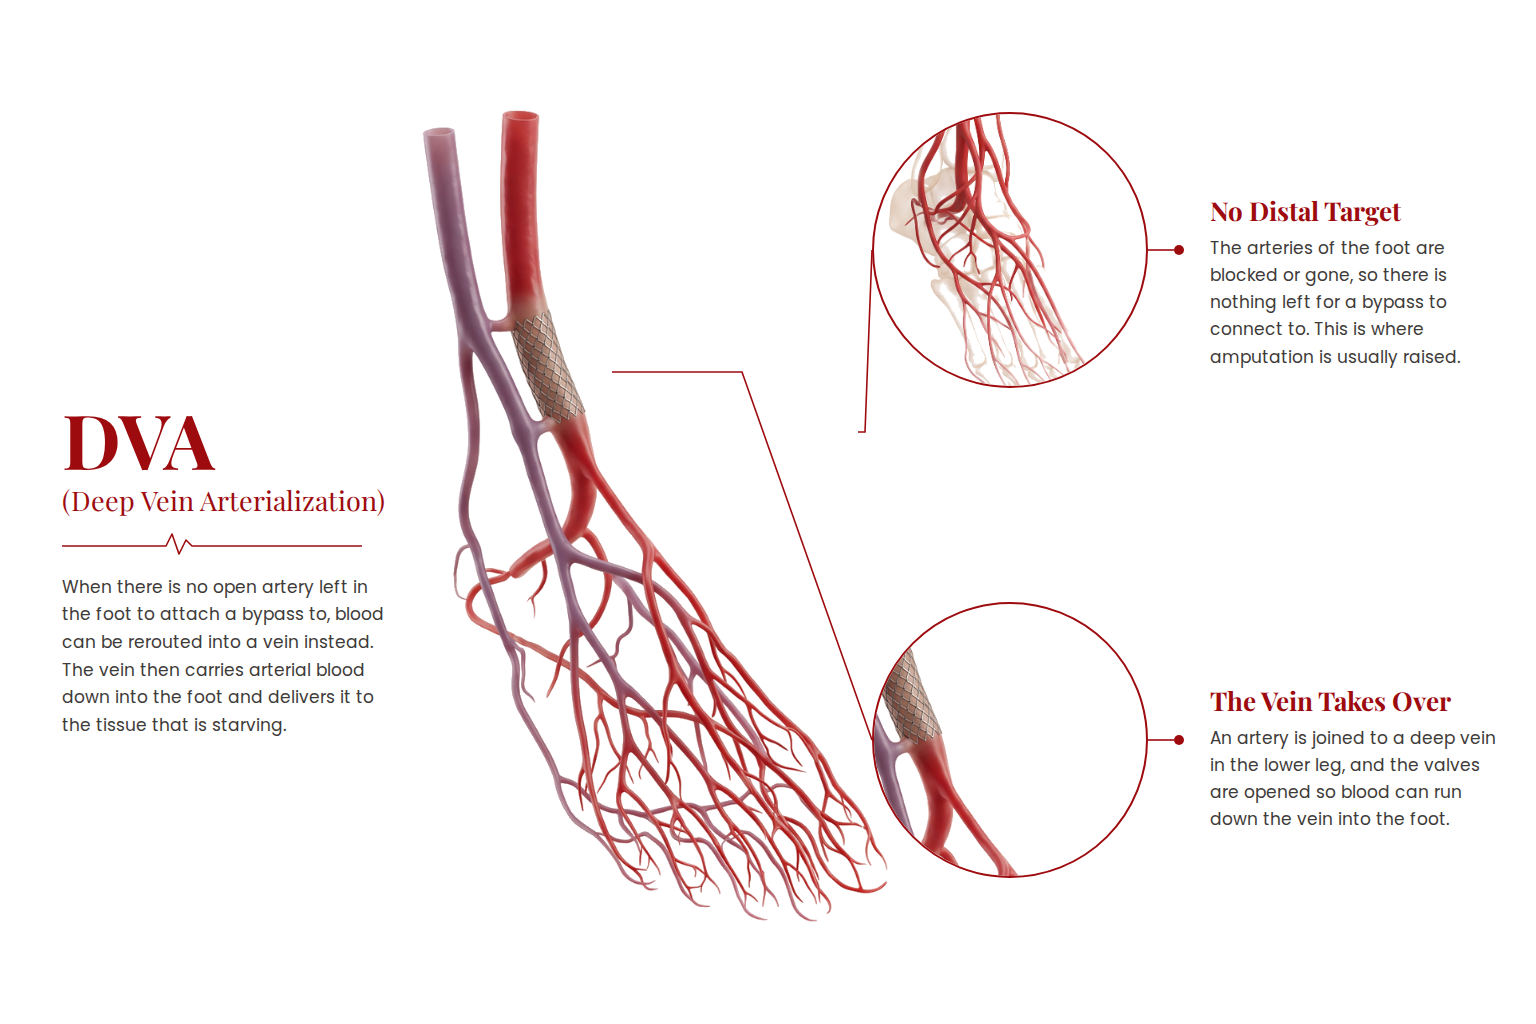
Here is the part that often gets missed. No distal target means there is no open artery left down in the foot to attach a bypass to. It does not mean there is nothing left down there. Running alongside every one of those dead arteries is a vein, and in most of these patients those veins are wide open and perfectly healthy.
That is the opening, and it is a real one. When there is no artery left to work with, a vein can be made to do the job. The procedure is called transcatheter arterialization of the deep veins, or deep vein arterialization for short. The system we use to do it is called LimFlow.
LimFlow is a set of instruments built for this one job. It includes the catheters that make the crossing from the artery into the vein, the tool that clears the valves out of the way, and the covered stents that hold the new channel open. It is not an off-label workaround or a piece of equipment borrowed from another operation. The FDA approved it in 2023 for exactly this situation, after a trial in patients who were facing amputation and had run out of other options.
We’ll take you through it the same way we would in clinic: how it works, who it helps, and what the results honestly look like. By the end you should know whether this is worth asking about, for you or for someone you love.
And if you’re deciding about an amputation this week, go straight to the section on second opinions near the bottom and call us at 305-279-2621. The rest of this will still be here afterward.
Patient identifiers have been removed, and every case is different. The trial results quoted later describe groups of patients, not any one person.
The main text is written for patients and families. A few sections end with a technical note for physicians. Skipping those costs you nothing.
How a vein took over and the foot got its blood back
The short version is that our team was able to restore blood flow to a foot that had none. We did it through a vein.
The arteries in this leg were beyond repair, which left nothing to attach a bypass to and nothing for a catheter to reopen. So we left them where they were, took the vein running alongside, joined the two together above the blockage, and disabled the one-way valves that would otherwise have stopped blood dead in that direction. Then we sent arterial blood down the vein and into the foot.
A wound on a foot with no blood supply will not heal, however good the dressings are and however careful the wound team is. Once the blood is flowing again, the rest becomes possible.
Why patients are told there are no arteries left to fix
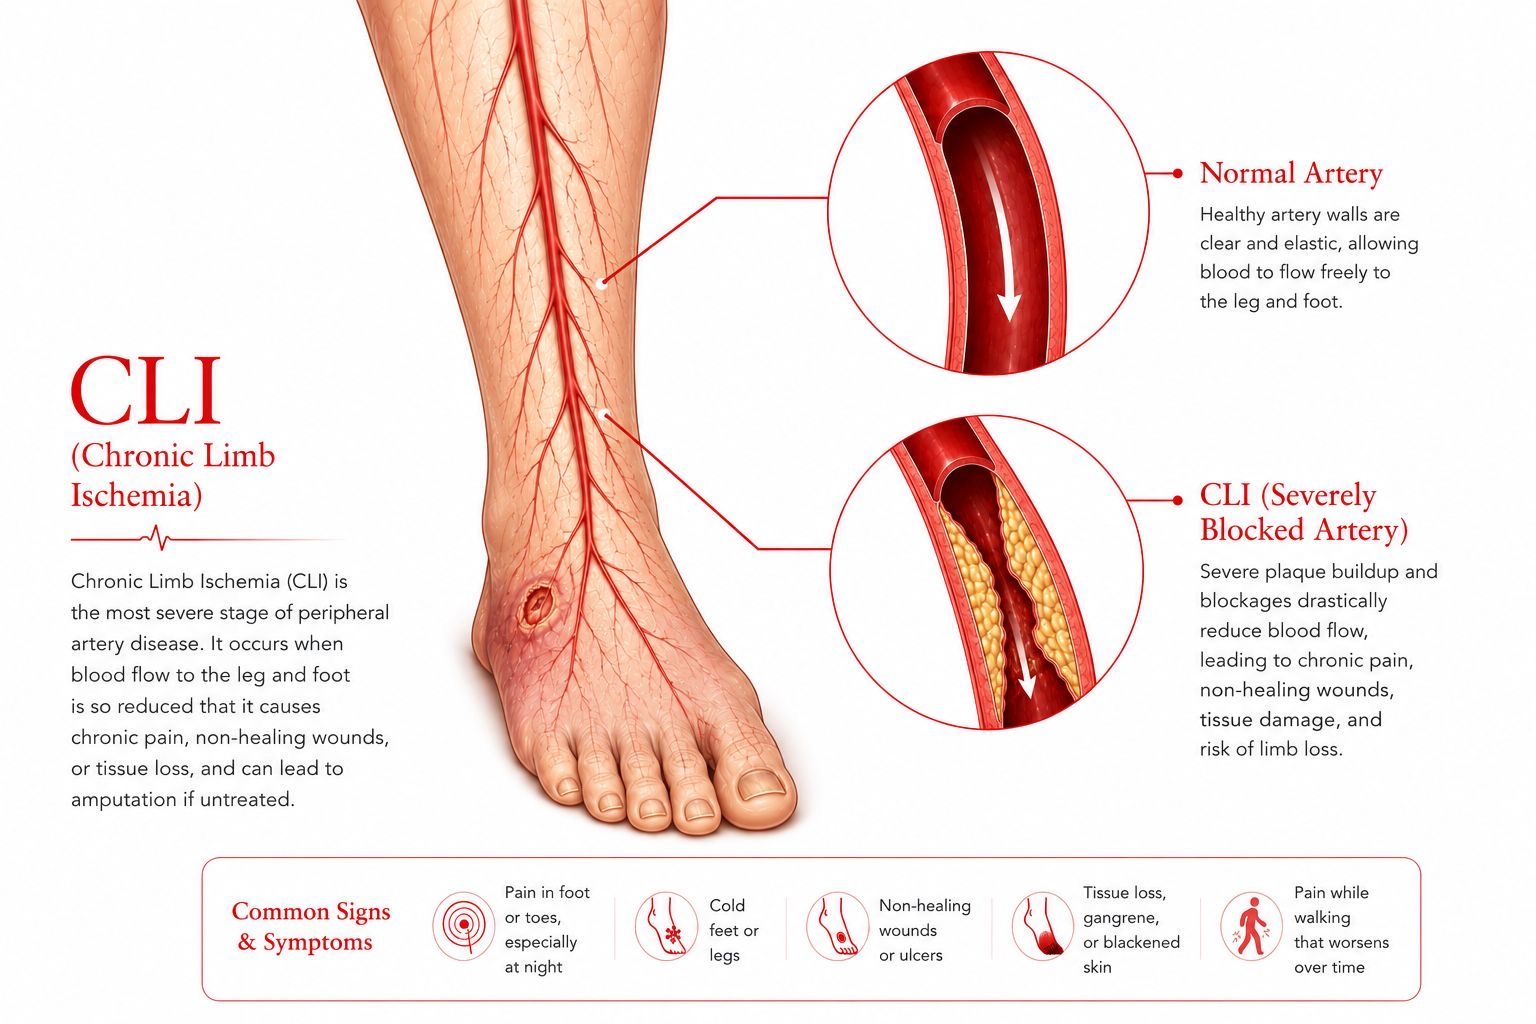
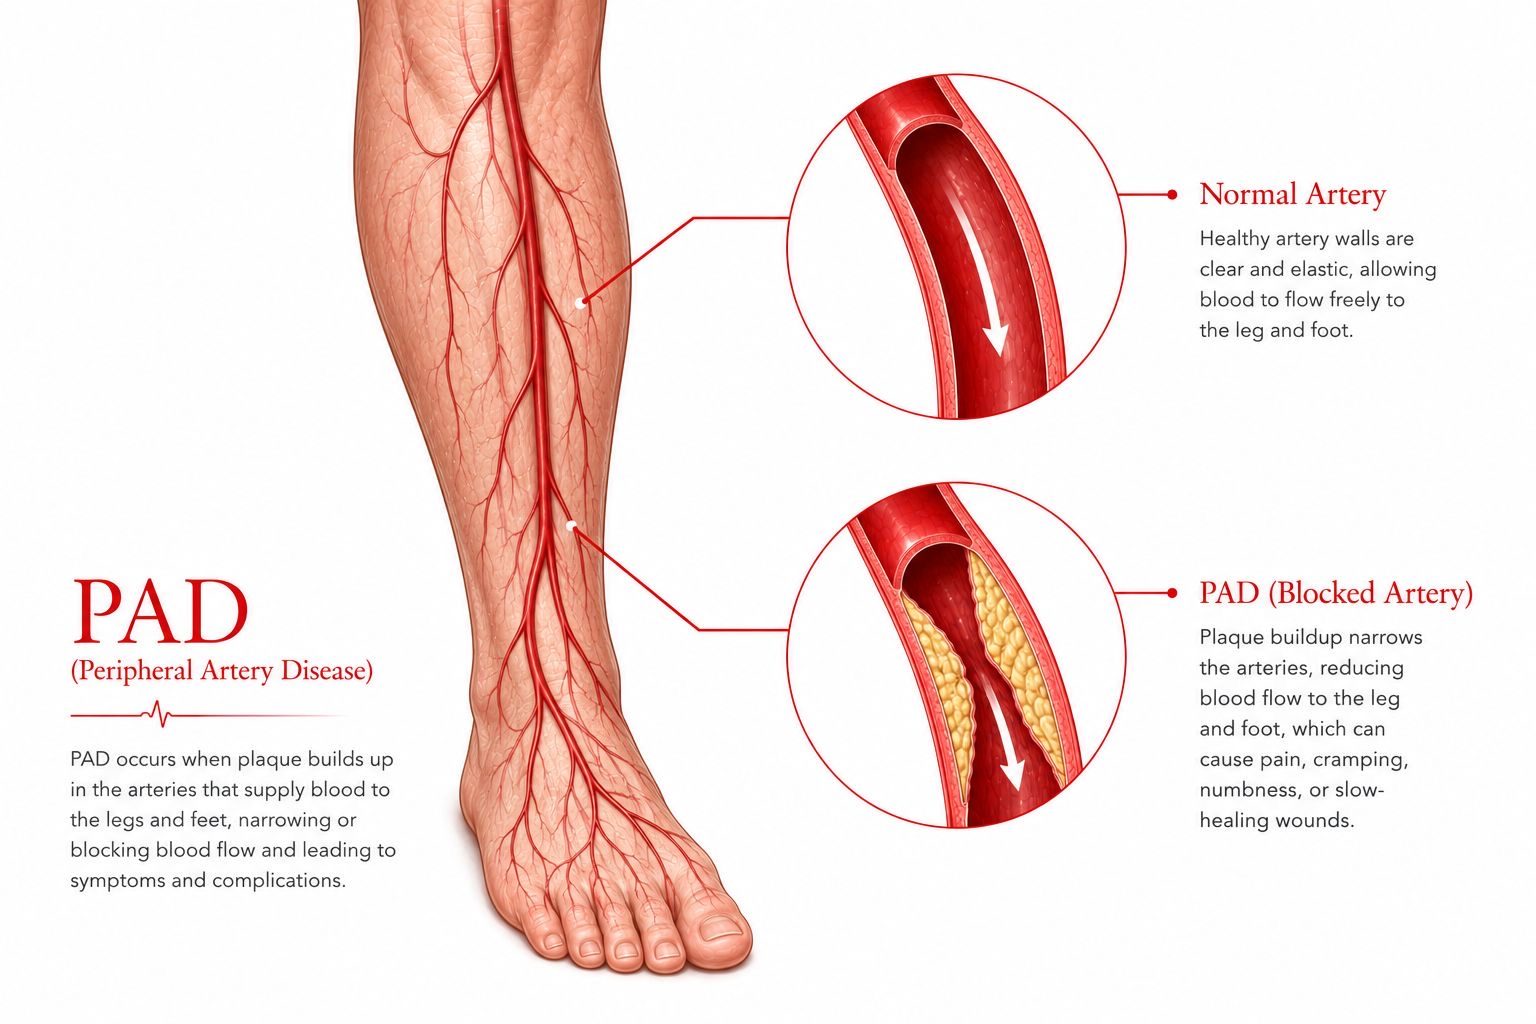
Peripheral artery disease is plaque narrowing the arteries of the leg. Left long enough, the foot stops getting enough blood even while you are sitting still, wounds stop closing, and tissue begins to die. At that stage it has a name, chronic limb-threatening ischemia, or CLTI.
In most cases there is something to be done about it. A blockage in the thigh or behind the knee can usually be opened from the inside, either by inflating a small balloon to push the narrowing open or by leaving a stent, which is a tiny mesh tube that props the artery open. It can also be bypassed surgically. Those patients do well.
A smaller group of patients hear something different. In them the disease has run all the way down into the tibial and pedal vessels, which are the small arteries in the calf and the foot, and the arteries at the bottom of the leg are no longer usable. These are the patients who get told they have no options.
It is worth saying what that phrase actually means, because it is narrower than it sounds. Both of the standard treatments need somewhere to land. A bypass is a new channel, made from a piece of the patient’s own vein or from a synthetic tube, and it has to be attached to a healthy artery below the blockage. Catheter treatment works by threading a thin tube through the blood vessels from a small puncture, so it needs an open artery to travel through and something worth opening at the end of it. When the arteries in the foot are gone, neither of those has anywhere to go.
So “no options” is really a statement about those two operations. It is not a statement about the leg, and it is not a statement about the patient. Running out of arteries and running out of options are not the same thing, and this is the exact situation deep vein arterialization was designed for.
We see this pattern most often in patients with diabetes and in patients on dialysis, and it is easy to miss. The larger arteries in the thigh and behind the knee can look perfectly reasonable on a CT scan while the foot below them is struggling. That is why we ask to see the angiogram itself rather than the report, and why a case that looks closed on paper is often worth a second look.
| Clinical note. No-option CLTI here means Rutherford class 5 or 6 disease with an absent or unreconstructable distal arterial target, confirmed on angiography and adjudicated as ineligible for conventional endovascular or surgical revascularization. This designation is distinct from technically difficult disease, and the distinction matters because deep vein arterialization is indicated only after conventional options are exhausted. Desert foot with an occluded pedal arch and no reconstitution is the archetype. |
Deep vein arterialization: how a vein does the work of a blocked artery
Arteries carry blood out from the heart, and veins carry it back. That is how the circulation is meant to work.
But that distinction matters far less than you would expect to the tissue at the end of the leg. A cell needs oxygen delivered to it. It has no way of knowing whether the vessel that brought it was an artery or a vein, and it does not behave any differently either way.
In most of these patients the veins are still open and healthy, even when every artery has failed. That is what makes this possible. The vein can do the artery’s job instead.
The result is a foot getting its blood supply backwards, through its own veins. It sounds like something that should not work, and yet it does.
| Clinical note. The procedure creates an arteriovenous crossover in the distal leg, most often posterior tibial artery to posterior tibial vein, using paired arterial and venous crossing catheters. A radiopaque self-expanding mesh is deployed in the target vein to distend it and act as a fluoroscopic target, and a needle is advanced from the arterial catheter into that mesh. Valvulotomy is performed retrograde along the target vein toward the foot, and the arteriovenous circuit and the venous outflow segment are lined with covered stents to create a durable conduit. Venous outflow branches may be selectively embolized where they demonstrably divert flow from the pedal target; routine coiling of all branches is not required, and selective embolization strategies vary between operators. The physiological result is arterialized venous perfusion of the foot. The mechanism of tissue oxygen delivery through an arterialized venous network is not fully characterized, though reversed exchange across the venous bed is the prevailing explanation. |
How we rerouted the blood flow, step by step
Step 1: No arteries left to work with

Figure 1. Every artery was blocked. One path remained.
Every artery that should have carried blood into this foot was blocked, which left nothing to attach a bypass to and nothing for a catheter to reopen.
An angiogram like this is where the standard options run out. It is where our work begins.
Saving legs, which is what limb salvage means, is what this practice is built around. It starts from the assumption that a leg is worth one more look before anyone gives up on it, and it is the reason we ask to see cases other people have already closed.
Step 2: Building a new route into the foot

Figure 2. LimFlow was used to reroute blood flow.
So we built a different path instead, and LimFlow was used to reroute the blood flow.
The connection is made between an artery and the deep vein lying alongside it. Covered stents, which are small fabric-lined tubes, then form a sealed channel so blood crosses from one vessel into the other without leaking into the tissue in between.
Step 3: Turning a vein into an artery

Figure 3. Veins became the new pathway.
Veins became the new pathway. The one-way valves inside the vein are the obstacle at this stage, because they exist precisely to stop blood travelling in this direction, so they are disabled on the way down.
Once they are out of the way, the vein can carry the new supply to tissue that has been starving.
Step 4: Blood flow reaching the foot again

Figure 4. Blood flow restored.
Blood flow was restored. The foot was receiving blood again, through a vein.
This is the image that changes what the next appointment is about. Instead of scheduling an amputation, the conversation turns to wound care.
| Clinical note. Intraprocedural confirmation is angiographic and hemodynamic. What matters on completion runs is opacification of the arterialized venous network in the foot with a defined outflow, not simply a patent conduit. The foot then enters a transitional phase over roughly six to twelve weeks during which edema is expected and the venous bed remodels. Wound healing characteristically lags perfusion, and premature pessimism during that window is a known pitfall. Surveillance duplex and a planned reintervention strategy are part of the therapy rather than a sign of failure, and the reintervention burden in this population is substantial. |
What the research shows about saving a foot this way
There is something you should know about the figures that follow. They come from the clinical trial that led to the FDA approving this procedure. They describe how the procedure performed across 105 patients at 20 hospitals. They are not this patient’s results, and this patient was not in that trial.
They are here for the same reason you would want to know about a medication’s trial before taking it. They are the best answer we have to what this procedure does, and does not, achieve.
This procedure is not experimental. It is also not routine, and both of those things are worth saying plainly.
The LimFlow System was approved by the FDA on September 11, 2023, under the agency’s strictest review pathway for medical devices (premarket approval, reference P220025). It is approved for patients with chronic limb-threatening ischemia who are facing amputation and who have no suitable surgical or catheter-based option.
Approval was based on a trial called PROMISE II, published in the New England Journal of Medicine. It enrolled 105 no-option patients across 20 US centers.
The procedure was technically successful in 99 percent of cases. Here is what the trial found at six months:
- Limb salvage was 76 percent. Roughly three in four patients still had the leg.
- Amputation-free survival was 66 percent. Two in three patients were both alive and had avoided a major amputation, meaning one above the ankle.
- Every patient started with an open wound or gangrene, meaning tissue that had already died. Of the 63 whose wounds could be assessed at six months, 16 had healed completely and 32 were still healing.
That is the encouraging half of the picture. The rest of it follows, because it is better heard now than discovered later.
About one in eight patients died within six months. That figure reflects how unwell this group of patients was rather than the safety of the procedure itself. Death rates were considerably higher among patients on dialysis.
Saving the leg does not always mean saving the whole foot. A toe or partial foot amputation may still be needed as part of wound care.
In the first few weeks the foot often looks worse before it looks better. Swelling, discoloration, and some skin breakdown are expected while the new circuit settles.
One more thing worth knowing. PROMISE II had no comparison group, because everyone enrolled received the procedure. That means there is no untreated group to measure the results against.
None of that makes the results less meaningful. These were patients facing the loss of a leg, and most of them kept it.
We give patients the difficult numbers alongside the good ones in clinic, and we are not going to do it differently here. If you are deciding about your leg, you need the whole picture rather than half of it.
Like any vascular procedure, this one carries risks. Those include bleeding, injury at the access site, clotting or narrowing of the new pathway, infection, and the risks that come with the blood-thinning medication it requires. The full device labeling is available from the FDA.
| Clinical note. PROMISE II (Shishehbor et al., NEJM 2023) was a prospective single-arm pivotal study, n=105, technical success 99.0 percent, six-month amputation-free survival 66.1 percent, Kaplan-Meier limb salvage 76.0 percent, complete wound healing in 16 of 63 (25 percent), with a further 32 of 63 (51 percent) healing. The wound denominator is patients with evaluable wounds at six months, not the full cohort. The dialysis-dependent CKD subgroup showed 36.2 percent mortality versus 8.6 percent without, which is the single most useful figure for calibrating expectations at consent. Absence of a control arm and the performance-goal design are the principal methodological limitations. |
Who this can help, and who it cannot
This procedure was built for a particular group of patients: those with chronic limb-threatening ischemia, an open wound or dead tissue on the foot, no remaining artery that a bypass or a catheter can use, and a major amputation as the alternative.
It is not a treatment for leg cramping when walking, and it is not a substitute for a straightforward balloon angioplasty or a bypass when one of those is still possible. If a simpler option exists for you, that is good news, and it is the one you should have.
There are also situations in which this is not the right answer. An infection in the foot that is not yet under control is one. A foot that has already lost too much tissue for a working result is another. Knowing that in advance is part of a careful evaluation rather than a door closing.
There are a few practical requirements as well. The veins have to be open and usable, with no clot in the vein that would become the new pathway. Patients have to be able to take the blood-thinning medication the new circuit requires, and to manage the follow-up, which includes regular ultrasound checks and a real possibility of a planned second procedure.
This is not the first thing we reach for. It belongs to one specific problem, and we say no to it when that problem is not the one in front of us.
But the option does exist, and it means the conversation does not have to end at the point where the arteries do.
Why a second opinion matters before an amputation
The reason to publish a case like this is not the technology.
It is that the phrase “no options” describes the tools available in a particular room on a particular day. It does not describe the patient.
A patient told at one center that nothing more can be done may still be a candidate at a center with the right equipment and training. That is worth knowing before agreeing to an amputation.
An amputation cannot be undone. It changes mobility, independence, and long-term health in ways that reach well beyond the leg. A second opinion costs no more than a consultation and a review of imaging you already have.
We would rather look and find nothing than not look. If there is a route in your leg, we want to find it. If there is not, we will tell you so directly, and you will go into the operation knowing the question was asked properly by people who wanted a different answer.
Talk to a limb salvage specialist in Miami-Dade or Homestead
At MVM Heart, Vein and Vascular Centers, our team pairs advanced diagnostics with compassionate, personalized care. We see patients at offices in Kendall (Miami) and Homestead, Florida, and serve Miami-Dade and the Florida Keys.
If you or someone you love has been told nothing more can be done for the circulation in a leg, bring us the angiogram before the amputation is scheduled. Not the report, the actual images if you can get hold of them. Most of what we need to know is on them.
Request a consultation or call 305-279-2621. We see patients at both our Kendall and Homestead offices. See our insurance information or download new patient forms before your visit.
MVM reviews no-option limb salvage cases and coordinates transcatheter arterialization of the deep veins with the appropriate treating center when that is indicated.
Referring physicians: we accept urgent limb salvage referrals and will review no-option angiography quickly. See information for referring physicians.
Frequently asked questions
I was told I need an amputation. Is a second opinion worth it?
Yes, it is worth it, and sooner rather than later. A look at the angiogram you already have can usually tell whether any option remains. If the answer is no, you’ve spent one consultation and you will know you left nothing unexplored. If the answer is yes, the whole decision changes.
Is it safe to send blood into a vein the wrong way?
Veins handle it better than most people expect. That’s the whole basis of the procedure.
Swelling in the foot and leg is expected in the weeks afterward as the vein adapts, and it’s managed rather than ignored. It’s also common for the foot to look worse before it looks better. Discoloration and some surface skin breakdown in the first weeks are part of the normal course, not a sign of failure. They are watched closely.
How long before the wound heals?
Longer than most people hope, and that’s worth preparing for rather than being surprised by. Blood flow comes back during the procedure, but tissue healing takes weeks to months, and steady wound care does much of that work. You aren’t on your own for that part.
In the trial, among wounds that could be checked at six months, a quarter had fully healed and about half were still healing.
Will I need another procedure?
Quite possibly, and that’s planned for from the start rather than treated as a failure. Follow-up ultrasound is part of the treatment, and repeat procedures to keep the new pathway open are common in this group. It means you’re being watched closely, not that something went wrong.
Does it work for everyone?
No, it does not work for everyone. In the trial, about three-quarters of patients still had their limb at six months. That’s a meaningful result for people at high risk of losing a leg, but it isn’t everyone.
Results depend on the condition of the veins, the amount of tissue already lost, the degree of infection control, and overall health, especially kidney function.
Is it covered by insurance?
The system is FDA approved for this use, and coverage is decided case by case. Our office can check your benefits before anything is scheduled.
Related reading
Critical Limb Ischemia · Peripheral Artery Disease · Vascular Ulcers · Our Services · Patient Education
This article describes a de-identified case and is provided for general educational purposes. Individual anatomy, treatment options, and outcomes vary, and no specific result is implied or guaranteed. Trial results describe groups of patients and do not predict any individual outcome. This is not a substitute for personalized medical advice. Always consult a qualified healthcare provider about your specific condition.
References
Shishehbor MH, Powell RJ, Montero-Baker MF, et al. Transcatheter Arterialization of Deep Veins in Chronic Limb-Threatening Ischemia (PROMISE II). *N Engl J Med.* 2023;388(13):1171-1180. doi:10.1056/NEJMoa2212754. https://www.nejm.org/doi/full/10.1056/NEJMoa2212754
U.S. Food and Drug Administration. LimFlow System, P220025. Premarket approval granted September 11, 2023. https://www.fda.gov/medical-devices/recently-approved-devices/limflowtm-system-p220025
Conte MS, et al. Global Vascular Guidelines on the Management of Chronic Limb-Threatening Ischemia (SVS/ESVS/WFVS). *J Vasc Surg.* 2019;69(6S):3S-125S. https://pubmed.ncbi.nlm.nih.gov/31159978/
Gornik HL, et al. 2024 ACC/AHA/Multisociety Guideline for the Management of Lower Extremity Peripheral Artery Disease. *Circulation.* 2024;149(24):e1313-e1410. https://www.ahajournals.org/doi/10.1161/CIR.0000000000001251
Fitridge R, et al. The intersocietal IWGDF, ESVS, SVS guidelines on peripheral artery disease in people with diabetes mellitus and a foot ulcer. 2023. https://iwgdfguidelines.org/wp-content/uploads/2023/07/IWGDF-2023-05-PAD-Guideline.pdf
Disclaimer: This article is general educational information, not medical advice for any specific person. For personalized guidance, please schedule a consultation or talk to your physician.
Disclaimer: This article is general educational information, not medical advice for any specific person. For personalized guidance, please schedule a consultation or talk to your physician.